

Substantial Angiographic Control Syringe: Key Considerations for Clinical Use
2026-09-07
Every second counts in the angiography suite, and the tools you rely on can make all the difference. The angiographic control syringe is one of those unsung heroes—quietly shaping precision, safety, and procedural flow. Yet not all syringes are created equal, and overlooking key design and clinical factors can lead to frustrating setbacks. From tactile feedback to contrast delivery consistency, each detail matters when you're navigating complex vascular territories. That's where INT steps in, rethinking what a control syringe should feel like in your hands. In this post, we'll unpack the essential considerations that elevate a standard syringe into a substantial clinical asset—so you can focus less on the equipment and more on the patient in front of you.
What “Substantial” Actually Means for Angiographic Control Under Pressure
In the cath lab, “substantial” is rarely a number you can pull from a textbook. A 60% residual narrowing after stent deployment might look trivial in a large right coronary artery but disastrous in a small, diffusely diseased left circumflex. Under the time pressure of an acute MI or a crashing patient, the eye tends to round down—we see what we hope is acceptable, not always what the fluoroscopy is actually showing. That's when the definition of substantial starts to bend.
The word itself implies a threshold, but that threshold moves with context. After treating a culprit lesion, a residual 40% stenosis with TIMI 3 flow might be called “not substantial” unless there's a dissection flap or the vessel is the only remaining conduit to viable myocardium. Conversely, a 50% lesion in a proximal LAD during elective angiography might be labeled substantial enough to warrant FFR or IVUS before committing to PCI. The pressure isn't just hemodynamic; it's the pressure to finish, to avoid complications, to make a decision the next operator won't second-guess.
So when someone says “no substantial residual disease” on the report, what they often mean is: given this patient, this vessel, and this moment, the remaining narrowing doesn't appear to threaten flow or require immediate action. It's a judgment dressed as a measurement—and under pressure, that judgment deserves a second look.
Contrast Viscosity vs. Plunger Resistance: Why the Wrong Syringe Slows You Down
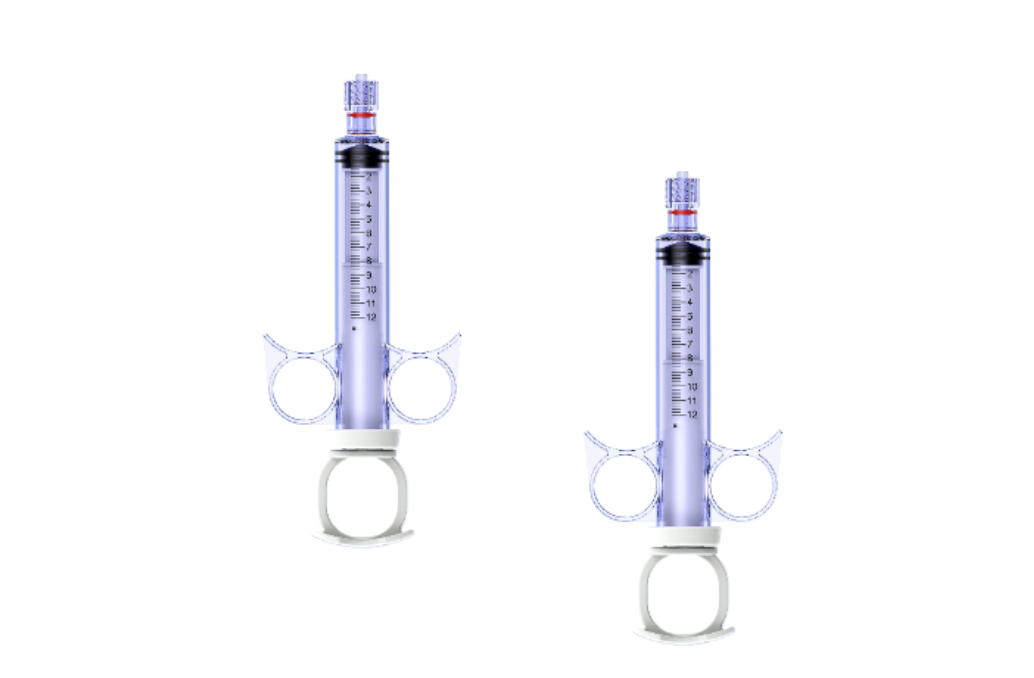
Many people assume a syringe's speed depends only on the fluid's viscosity, but plunger resistance often matters just as much. A thick, viscous liquid naturally demands more force to move through the needle, yet a poorly fitted or overly stiff plunger can add friction that makes even low-viscosity samples feel sluggish. When the two factors combine—say, a high-viscosity reagent paired with a syringe that has noticeable plunger drag—the user ends up fighting the tool instead of focusing on precise aspiration or dispensing.
Choosing the wrong syringe doesn't just slow each draw; it also disrupts rhythm and increases the chance of hand fatigue or uneven flow. A low-resistance plunger, matched to the fluid's viscosity, lets you maintain a steady pace without having to push or pull excessively. By comparing how the liquid resists flow against how the syringe's own components resist movement, you can spot the real bottleneck and pick a model that keeps your workflow moving at the intended speed.
Luer Lock Stability: A Small Connection That Becomes a Big Risk in Long Procedures
The Luer lock connector is one of those components that rarely draws attention until it fails. In a short procedure, a properly tightened Luer lock holds without issue, but over the course of hours—especially in vascular access, infusion therapy, or extracorporeal circuits—micromovements, pressure fluctuations, and material fatigue start to work against the thread. What begins as a secure mechanical fit can gradually loosen, and because the change is often subclinical, it goes unnoticed until the line separates or leaks.
Long procedures amplify several failure modes at once. Repeated syringe changes, patient repositioning, and pump-induced vibrations create a slow unscrewing effect, while temperature shifts and exposure to lipids or solvents can alter the plastic’s grip. A partially disengaged Luer may still appear connected externally, yet it permits air ingress, blood leakage, or a drop in infusion pressure. In critical settings like hemodialysis or chemotherapy delivery, this can mean underdosing, contamination, or an air embolism—risks that are entirely out of proportion to the size of the connector.
Mitigation demands more than a final hand-tight check. Some teams adopt locking mechanisms with secondary retention clips or use Luer-activated valves that reduce open manipulation time. Others integrate periodic torque checks into the procedural checklist, especially after any line manipulation. Ultimately, the goal is to treat the Luer lock not as a set-and-forget fitting but as a dynamic interface that requires monitoring throughout the case. When a procedure stretches beyond a couple of hours, the smallest thread can become the weakest link.
Can Ergonomics Prevent Fatigue Without Sacrificing Injection Precision?
Ask any clinician who performs dozens of injections a day and they'll tell you the same thing: hands tire long before technique falters. The real question isn't whether ergonomics matters, but whether a device can be shaped to the natural mechanics of the hand without introducing wobble, drift, or overshoot at the needle tip. A lighter grip, a shorter reach to the plunger, a barrel that sits low in the palm—these adjustments reduce muscle strain, but they also alter the fulcrum points that steady the needle during aspiration and delivery.
Manufacturers often chase comfort by adding softer contours or rubberized textures, yet precision depends on stiffness and feedback. The compromise shows up in details like trigger resistance: too light and the thumb fires before the brain confirms placement; too heavy and the wrist compensates, pulling the tip off target. Some newer designs split the difference by moving the injection force to the larger forearm muscles while keeping the fingers in a neutral, locked position. That shift preserves the tactile endpoint—the subtle resistance change when the needle passes through tissue layers—without demanding a white-knuckle grip.
In practice, the devices that stand out are the ones that let the hand rest rather than constantly adjust. A slightly angled needle hub, a plunger that indexes with a soft click instead of a hard stop, a weight distribution that leans into the thenar eminence—these small choices accumulate into a noticeable difference by the third hour of use. And crucially, they do it without masking the mechanical signals that tell an experienced operator exactly where the tip is. Fatigue prevention and injection precision aren't opposing goals; they're both downstream of the same thing: a tool that works with the hand's anatomy instead of against it.
Air Embolism Prevention Isn't Just About Careful Filling—It's About Cap and Plunger Design
Most clinicians focus on tapping the barrel and expelling the last visible bubble before injection, but that ritual misses where air actually enters in the first place. The cap and plunger interface is a primary source of microemboli. A cap that snaps on with a dead space cavity traps air, and a plunger tip that doesn’t fully mate with the cap during priming leaves a residual pocket that gets pushed forward as a bolus.
Design choices matter more than technique in many cases. A plunger with a convex nose that matches a concave cap cavity forces air out through the fluid path rather than letting it collect around the rim. Low-friction coatings help too, because they prevent the plunger from skipping and creating vacuum pockets during aspiration. When those two parts are poorly matched, even a slow, careful fill draws air in around the side seals.
Then there’s the cap’s venting behavior. Some caps are designed to let air escape during priming without allowing blood or medication to leak, but if the vent path is too narrow or positioned off-center, air gets compressed and rebounds into the barrel later. A well-engineered cap and plunger pair reduces the need for aggressive tapping or overfilled syringes, shifting the focus from operator skill to predictable geometry.
Single-Use Considerations: Material Degradation and the Cost of Reuse
Single-use products are typically engineered for a narrow performance window. When they are pushed into repeated service, the materials often degrade in ways that are not immediately visible. Plastics develop micro-fractures at stress points, elastomers lose elasticity, and surface coatings wear thin. Even if an item looks intact after a quick rinse, its structural integrity may already be compromised, leading to leaks, breaks, or contamination risks that far outweigh the apparent savings.
The cost of reuse is not just financial. There is a hidden operational burden: staff must inspect, clean, and store items that were never meant to be reused, and those steps rarely follow validated protocols. In regulated settings, the liability from a failed “reused single-use” component can be substantial. Meanwhile, the actual material cost saved per unit is often pennies, making the practice a poor trade-off once degradation, labor, and risk are accounted for.
FAQ
A substantial control syringe is built to handle repeated high-pressure injections without barrel distortion or plunger blowback. It typically has a thicker wall, a locking mechanism rated for power injector use, and a low-compliance plunger that holds its position under backpressure. Unlike a routine syringe, it is designed to stay stable when connected to a manifold or contrast line during dynamic imaging runs.
If the syringe is not rated for the pressures generated by a power injector, the barrel can expand slightly and the plunger may leak, causing inconsistent contrast flow and poor opacification. A substantial syringe with a pressure capacity above the injector's peak output maintains a tight seal and steady flow, which is critical for visualizing small vessels or overcoming resistance in tortuous anatomy.
Look for a secure, audible or tactile locking hub that prevents accidental disconnection, a clear barrel that allows immediate air bubble detection, and a plunger design that resists spontaneous movement when the injector is idle. Some models also include a pressure-limiting vent or one-way valve to reduce the chance of air embolism or fluid reflux into the contrast line.
Not always. Injector interfaces vary by manufacturer, and even small differences in thread pitch, locking collar diameter, or ram engagement depth can lead to poor seating or detachment under pressure. Before use, confirm that the syringe model is listed by the injector manufacturer for the specific pump, and perform a low-pressure test fill to check for leaks or wobble at the connection.
Most substantial control syringes have a maximum fill line that should not be exceeded because overfilling can reduce the plunger's travel range and create air traps. Contrast should be warmed to body temperature or per manufacturer guidance before filling to lower viscosity, but avoid prolonged exposure to heating cabinets that might degrade the contrast or soften the syringe polymer. For lengthy cases, plan to refill with freshly warmed contrast rather than leaving a full syringe on the table for hours.
High-contrast, graduated markings positioned close to the injection site help the operator confirm the delivered volume at a glance, especially during subtle hand injections. A plunger with controlled friction moves smoothly without sticking or free-falling, which translates into predictable flow rates and less chance of overshooting the intended contrast volume when switching from power to manual control.
Forcing the syringe onto an incompatible injector head, pulling back the plunger too rapidly during filling, and touching the sterile tip or connector after removing the cap are frequent errors. Leaving the syringe connected to a patient line while repositioning the table can also put torque on the hub and create microcracks that fail under pressure. Always keep the Luer lock and injector interface clean, dry, and protected until the moment of connection.
A loose or cross-threaded connection can leak contrast, draw air into the line, or detach under power injection pressure, causing a potentially serious interruption during a critical imaging sequence. A quick visual and tactile check of the locking collar and a low-volume test injection at the start of each run helps confirm that the syringe is fully seated and that no contrast is weeping from the hub before high flow is initiated.
Conclusion
In high-pressure angiography, a syringe that feels robust on the bench may still fail where it matters most. The term substantial here refers less to bulk and more to how the barrel and plunger behave when pushing viscous contrast through a catheter at several hundred psi. A stiff plunger paired with high-viscosity media creates unnecessary hand strain and makes fine flow adjustments jerky, while a well-matched plunger resistance keeps injection smooth without fighting the fluid. Equally overlooked is the Luer lock; over the course of a long intervention, repeated torque and small movements can loosen a seemingly secure connection, risking leaks or disconnection at the worst moment. A solid lock that stays tight through manipulation is not a luxury.
Ergonomics directly affects precision. If the flange shape forces an awkward grip, operators compensate by altering injection angle or speed, which degrades control. A syringe designed for a natural hand position allows sustained, accurate delivery without forearm fatigue. Air embolism prevention goes beyond careful filling; vented caps that let air escape during priming and plunger tips that wipe the barrel wall reduce the chance of microbubbles reaching the patient. Single-use labeling exists for a reason. Repeated sterilization and exposure to contrast agents can degrade polymer seals and barrel clarity, increasing the risk of particulate shedding or loss of pressure integrity. Reusing a disposable angiographic syringe may save inventory cost but introduces clinical risk that no protocol should accept.
Contact Us
Contact Person: Jeffrey
Email: [email protected]
Tel/WhatsApp: 86-0633-2230056
Website: https://www.sd-intmedical.com

